

 Türkçe
 Deutsch
 Français

Short answer: Yes, hair transplants work on the crown. Grafts taken from the back and sides of the head resist the hormone behind pattern baldness and keep growing in the crown, and in experienced hands crown graft survival is comparable to the front of the scalp. Whether the result looks like a success depends on planning: donor capacity, how the density is spread, and whether the surrounding hair loss is managed. Below we cover what the success rate really means, who is a good candidate and why some crown results disappoint. If you have already had surgery and want to know what happens month by month, see our crown hair transplant recovery timeline.
Updated 11 November 2026. Meet our physician, Dr. Barış Duman.
Type “do hair transplants work on the crown” into a search bar and you can watch two industries argue with each other. Clinics selling package deals will tell you the crown is no different from any other part of the scalp — send photos, book a date, done. Forums will tell you the opposite: that crown work is where grafts go to disappear, that results always look thin, that you will be back for a second session within two years. The truth sits between the sales pitch and the horror stories, and if you are trying to make a real decision about your own head, you deserve to hear it plainly.
So here is the plain version — the direct answer first, then the honest fine print that decides whether that answer applies to you.
Can You Get a Hair Transplant on the Crown? The Short Answer
Yes, hair transplants work on the crown. Grafts are taken from the donor area at the back and sides of your head, a zone that is genetically resistant to DHT, the hormone that drives pattern baldness. Those follicles keep their resistance wherever they are moved. Implant a healthy graft into the crown with the right angle and direction, and it will grow there for the long term, just as it would have kept growing where it came from.
The honest part is what comes after that sentence. A crown hair transplant works, but it works under conditions: enough donor supply, a stable or medically managed hair loss pattern, realistic density expectations, and a medical team that understands the crown’s spiral architecture. When those conditions are met, crown results can be excellent. When they are ignored, the crown is where transplants disappoint most often — not because the biology fails, but because the planning does. That gap between “the grafts grew” and “the patient is happy” is the entire story of crown surgery, and it is why we wrote a full complete guide to crown area hair transplants alongside this more focused question-and-answer piece.
Why the Crown Behaves Differently From the Hairline
Ask most people what they picture when they think about a hair transplant and they describe a hairline. That framing quietly shapes expectations, because the hairline and the crown are two very different surgical problems wearing the same name.
At the hairline, hair grows forward in a broadly consistent direction, and the frame of your face does most of the visual work. A well-designed frontal zone can transform how you look with moderate density, because you view it head-on and the hairs layer over each other in one direction.
The crown is the opposite case. Hair there grows in a spiral — the whorl — radiating outward in every direction from a central point. You view it from above, under overhead lighting, which is the least forgiving angle that exists. There is no facial frame to help, no single direction of layering to create the illusion of fullness. Every centimeter of coverage has to be earned with actual, correctly angled hair. This is the core reason crown hair transplants are more challenging than the hairline, and why a clinic’s crown results tell you more about its skill than its hairline portfolio ever will.
Crown Hair Transplant Success Rate: What the Numbers Actually Mean
You will see clinics advertise a high crown hair transplant success rate. Those figures usually measure something narrower than most patients assume. It refers to graft survival — the percentage of transplanted follicles that take root and produce hair. In experienced hands, crown graft survival is comparable to the front of the scalp.
Here is the distinction that matters: graft survival is not the same as patient satisfaction. A crown procedure can have excellent graft survival and still look underwhelming if too few grafts were spread across too large an area, or if the surrounding native hair kept thinning and unveiled the transplant’s edges. Conversely, a well-planned crown with the same survival rate can look convincingly full because density was concentrated intelligently and the loss pattern was managed with medication.
So when you ask “is crown hair transplant successful,” split the question in two. Biologically successful — will the grafts grow? Almost always, in competent hands. Aesthetically successful — will it look the way you hope? That depends on planning, donor supply, and expectations, which is exactly where the rest of this article lives. At Hairpol, we would rather explain that distinction before the procedure than apologise for it afterwards.
Why No Clinic Can Honestly Quote You One Percentage
Graft survival is the fraction of transplanted follicular units that establish a blood supply in their new position and go on to produce hair through the normal cycle. A graft that fails does not fall out visibly — it simply never returns after the shedding phase that follows every transplant.
Here is where the counting gets slippery. Almost nobody actually counts. Measuring true survival requires tattooed reference points, fixed-frame macro photography and a hair count inside a defined box at baseline and again a year later. Research groups do this. Commercial clinics, as a rule, do not — they estimate from experience and outcome photographs. So when a clinic quotes you a survival rate, the honest translation is usually “this is what results like yours have tended to look like in our hands.”
The band most often cited for competent modern work sits somewhere between 85 and 95 percent. Those published ranges come from studies with different definitions, different follow-up windows, different techniques and small patient numbers. Some counted hairs; some counted grafts. Some measured at nine months, before the crown had finished, which systematically understates the result. Some excluded smokers and diabetics from the sample, which flatters it. The honest thing to say about that band is that it describes a population, not you. Your own figure depends on your scalp laxity, your vascularity, your hair calibre, your medical background, how long your grafts sat outside the body, how densely they were packed, and what you did during the two weeks that followed.
At Hairpol we do not give patients a survival percentage before the operation, and you should be wary of anyone who does. What we do give is a guarantee certificate covering the growth of transplanted hair in the transplanted area for 18 months, under the conditions on our guarantee page; density and the final result still vary from person to person. We wrote a fuller account of how survival is defined and what a clinic can genuinely do to protect it in graft survival rate: what it means and how good clinics maximise it.

The Whorl Pattern: A Small Spiral With Big Consequences
The whorl deserves its own section, because it is the single most technical reason crown outcomes vary between clinics.
Natural crown hair does not simply point in one direction. It spirals — clockwise in most people, counterclockwise in some, occasionally as a double whorl with two centres. Within that spiral, the angle of each hair shifts continuously: nearly flat at the outer edges, progressively more upright toward the centre. Recreating this means the surgical team must change the angle and rotation of their implantation continuously across the zone, sometimes graft by graft.
When the whorl is rebuilt correctly, transplanted crown hair layers over itself the way natural crown hair does, and the eye reads it as ordinary. When it is implanted in uniform rows at uniform angles — which is faster, and cheaper in surgical effort — the result looks flat, brushed, and subtly wrong even to people who cannot say why. If you have ever seen a crown result described as looking like doll hair, a mishandled whorl is usually the reason. This is a craftsmanship variable, invisible in graft-count quotes, and it is one of the first things to evaluate in any clinic’s healed crown photos.
Donor Capacity: The Budget Behind Every Crown Decision
Your donor area holds a finite supply of safely extractable grafts, and how many it can give varies from person to person. Every crown decision is really a budgeting decision made against that limit.
The crown is expensive territory. Because it is a wide, curved surface viewed from above, it consumes grafts at a rate that surprises almost everyone: a modest crown might need 1,000 to 1,500 grafts, a moderate one 1,500 to 2,500, and an advanced, extended crown can absorb 2,500 or more on its own. We break the estimates down properly in our guide to how many grafts you need for a crown hair transplant, but the strategic point matters more than the arithmetic: grafts spent on the crown are grafts you can never spend on the hairline or mid-scalp later.
This is why responsible planning treats your donor area as a lifetime resource rather than a single-procedure inventory. If your loss pattern suggests the front will eventually need work too, a good surgeon plans both zones on paper before extracting a single graft — even if the crown is all you feel today. The patients who end up trapped, with a bald frontal zone and an empty donor bank, are almost always the ones whose first clinic spent freely on the crown without asking what the next decade would demand.
Progressive Hair Loss: The Crown Is a Moving Target
Here is the variable most patients underestimate, and the one behind a large share of crown disappointment: the crown you have today is not the crown you will have in five years.
Pattern baldness in the crown expands outward from the whorl like a slow ripple. If you transplant into a thinning crown while that ripple is still moving, the transplanted island stays — it is DHT-resistant — but the native hair around it keeps retreating. The result, two or three years later, is a ring of bare scalp around a patch of transplanted hair. The procedure did not fail. The planning did, because it treated a moving target as a stationary one.
There are two honest responses to this. The first is medication: finasteride, and to a lesser degree minoxidil, can stabilise the pattern and protect the native hair surrounding your grafts, which is why many surgeons consider medical stabilisation close to a prerequisite for younger crown patients. Supportive clinic treatments such as PRP and mesotherapy — the kind offered through our hair treatments department — can reinforce that foundation. The second response is timing: sometimes the right decision is to wait a year or two until your pattern declares itself. A clinic that never mentions either option is not planning your crown; it is selling it.
Age and Timing: When a Crown Transplant Makes Sense — and When to Wait
Age changes the crown calculation more than it changes almost any other transplant decision.
In your twenties, a thinning crown is usually an early signal of a pattern still unfolding. Transplanting it immediately is one of the classic mistakes of hair restoration: the loss keeps expanding, the graft budget has already been spent, and the young patient faces revision surgery before thirty. For most men under about 27 with active crown loss, the sober advice is stabilise first, transplant later — and any clinic that rushes you past that step is optimising for its schedule, not your scalp.
In your thirties and forties, the picture usually clarifies. The pattern has largely declared itself, response to medication is known, and a surgeon can read your family history against your current Norwood stage with reasonable confidence. This is the age band where most successful crown work happens, and where a single well-planned session has the best odds of being the only one you need.
Beyond fifty, the question flips from stability to supply: the pattern is usually settled, but donor capacity and hair characteristics need honest assessment. Plenty of patients in their fifties and sixties get excellent crown results — the deciding factor is the donor bank, not the birthday.
Who Is a Good Candidate for a Crown Hair Transplant?
Pull all of those threads together and a fairly clear portrait of the strong crown candidate emerges. You are likely a good candidate if most of the following describe you:
- Your hair loss has stabilised — either naturally with age or through at least 8 to 12 months of medication with documented results.
- Your donor area is strong: dense, healthy back-of-scalp hair with enough capacity to cover the crown and still leave reserves for the front.
- Your crown loss is defined rather than diffuse — a clear thinning zone with reasonably intact surroundings responds better than widespread, patchy miniaturisation.
- Your expectations are calibrated: you are aiming for solid, natural coverage that ends the shine and the self-consciousness, not for the crown density of a teenager.
- You accept the timeline — crown results mature slowly, and you will need 12 to 18 months of patience before judging the outcome.
Notice what is not on the list: a particular age, a particular Norwood number, or a particular graft count. Candidacy is a profile, not a single measurement, and at Hairpol the consultation exists precisely to build that profile honestly — including telling you when the answer is “not yet.”
Who Is Not a Good Candidate — at Least Not Yet
The mirror image of that list matters just as much, because the crown punishes poor candidacy more brutally than the hairline does.
You should pause — not necessarily forever, but for now — if your crown loss is recent and clearly still progressing, especially in your early or mid twenties. If you have never tried stabilising medication and are unwilling to consider it, understand that you are choosing a higher probability of the ring-around-the-island outcome, and the plan should be adjusted accordingly. If your donor area is weak, diffuse, or already partially depleted by earlier procedures, the math may simply not support a crown project at meaningful density. And if what you actually want is the front — the frame you see in every mirror and photo — it is usually wiser to prioritise that zone first, a trade-off we examined in detail across our crown planning articles.
None of this means the door is closed. It means the sequence matters: stabilise, reassess, then transplant if the numbers work. A refusal or a deferral from a serious clinic is not a rejection — it is the cheapest protection you will ever get against an expensive regret.
What Moves Your Own Crown Result: Blood Supply, Density, Smoking and the First Two Weeks
Grafts survive because tiny vessels in the recipient bed reconnect and feed them. The crown, particularly in men who have been bald there for a decade or more, tends to have thinner, less vascular, sometimes shinier skin than the frontal scalp, because long-standing baldness quietly reduces the local blood supply and stiffens the tissue. That is why two men with identical graft counts can land in different places. The 34-year-old with a crown that thinned over the last three years, with soft skin and visible miniaturised hairs still present, usually grows better than the 52-year-old with fifteen years of smooth, tight, shiny scalp in the same spot. Previous surgery adds another layer: a crown that has already been operated on carries scar tissue in the recipient bed, and scarred skin is less vascular than virgin skin.
Placement density. Packing grafts closer together makes the crown look better — right up to the point where it makes the crown grow worse. Every incision is a small injury to the blood supply of the area. Place them far apart and each graft has generous circulation; place them very close together and the incisions begin to compete for the same limited flow. Surgeons manage this by using moderate densities at the crown, sometimes concentrating a little more at the leading edge where the eye lands and easing off toward the centre of the whorl. A clinic that promises you both maximum density and maximum survival at the crown is promising two things that pull against each other.
Smoking and nicotine. Nicotine constricts blood vessels, and carbon monoxide from smoke displaces oxygen in the blood. Both act directly on the mechanism grafts depend on during the first days. No clean percentage exists for what smoking costs, but surgeons consistently observe slower healing, more prolonged redness and, in heavy smokers, patchier growth in the crown specifically. Vapes and nicotine pouches are not a workaround; the vasoconstrictor is the nicotine, not the smoke. The usual advice is to stop at least two weeks before the procedure and stay off it for at least two weeks afterwards, and to say so honestly at consultation if you cannot.
The first two weeks. A newly placed graft has no blood supply of its own. For roughly the first 48 to 72 hours it survives on fluid diffusing from the surrounding tissue; new vessels then grow in, and by somewhere around day 10 to 14 the graft is anchored. The practical list is short: do not let the grafts dry out, follow the washing protocol on schedule, sleep elevated and off the crown, keep sweat and friction away, avoid anything that spikes blood pressure, and do not pick a crust off early. After the fortnight, your survival number is largely fixed.
An unstable donor. In diffuse unpatterned alopecia (DUPA) the donor region at the back and sides is itself miniaturising, and grafts taken from it carry that instability with them. It is found by examining the donor area under magnification, which is why a consultation that never looks at the back of your head is not a consultation.
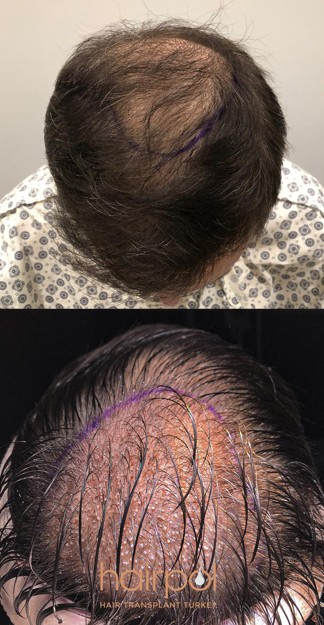
Why Do Crown Hair Transplants Fail? The Real Reasons
When people search “why crown hair transplant fail,” they are usually bracing for a biological answer — weak grafts, poor healing, bad luck. Biology does occasionally play a role. But in practice, most failed crowns trace back to human decisions, and they cluster into a short list.
Underestimated progression is the leading cause: transplanting a moving target without stabilisation, producing the isolated island effect described above. Under-grafting comes second — spreading 800 grafts across a zone that honestly needed 1,800, often because a package price was built around a number rather than a surface area. Wrong angles and ignored whorls produce the flat, unnatural look that technically grew but never convinces anyone. Poor donor management — overharvesting the safe zone or taking grafts from areas that will later thin — undermines both the crown and everything after it. And finally, neglected aftercare in the first two weeks, when grafts are still anchoring, can cost real survival percentage in a zone you cannot see or easily protect while you sleep.
Read that list again and notice the pattern: every major failure mode is preventable, and almost all of them are decided before or during surgery, not after. That is genuinely good news, because it means choosing carefully matters more than hoping.
How a Good Clinic Stacks the Odds in Your Favour
Prevention is just the failure list inverted, executed with discipline.
It starts with an honest map: assessing your loss pattern, your family history, your response to medication, and your donor capacity before quoting anything. It continues with a whole-scalp plan that budgets grafts across zones and decades, not just across one invoice. In the operating room, it means implantation that follows your whorl’s direction and shifts angle continuously — work where technique choice can genuinely help. Sapphire FUE uses sapphire blades to open small, precisely oriented channels that hold tight angle control across the spiral, while DHI implants each graft directly with a pen-like device, giving fine control over angle and depth in curved terrain. Both can rebuild a convincing whorl; what matters more than the acronym is the team’s experience using it on crowns specifically.
Finally, a good clinic is honest about staging. Some advanced crowns are better treated in two planned sessions than one heroic marathon, letting the first result mature before density is reinforced. That honesty extends past surgery into structured aftercare and follow-up. At Hairpol, crown patients leave with a written protocol and scheduled check-ins across the first year, because the crown’s slow timeline makes guided patience part of the treatment itself.
FUE Transplant for the Crown: How It Works
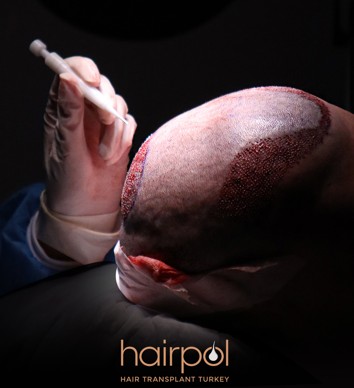
Most crown hair transplants today are done with FUE, follicular unit extraction, and it suits the crown well. Grafts are removed one by one from the donor area at the back and sides with a small punch and then placed into the thinning crown, so there is no linear scar and the extraction can be spread evenly across the safe zone.
That spread matters more for the crown than for most areas. Because a crown can take a large share of your lifetime donor supply, the way grafts are harvested decides how healthy the donor looks afterwards and how much is left for the front later. Careful FUE takes grafts in a dispersed pattern, so the back does not look thinned out even after a large crown session.
On the implantation side, FUE is a family rather than a single method. Channels can be opened with sapphire blades, or grafts can be placed with an implanter pen as described above. Either way, the crown-specific work is the same: following the whorl, changing angle across the spiral, and putting enough density in the centre so the area does not read as thin from above. The extraction method affects how grafts are collected. The angle work is what decides whether the crown looks natural.
A typical FUE crown session is a long day, with extraction first and implantation after, done under local anaesthesia. If you want to see how the day runs from arrival to aftercare, our overview of the FUE hair transplant process walks through each step.
Can You Get a Hair Transplant on the Crown Alone?
A practical question we hear constantly: can you get a hair transplant on the crown only, leaving the front untouched? Yes — crown-only procedures are common and entirely legitimate. Plenty of men keep a strong hairline for life while the crown thins behind it, and for them the crown is correctly the whole project.
The caveat is again about the future rather than the present. Before committing your donor budget to a crown-only plan, a surgeon should assess how likely your frontal zone is to need help in the coming decade — using your age, your miniaturisation pattern under magnification, and your family history. If the front looks secure, spend confidently on the crown. If the front looks like it is quietly following, the smarter plan may reserve grafts, stabilise medically, or sequence the front first even though the crown bothers you more today.
There is also a comfort worth naming: the crown is the easiest zone to be patient with. It sits where you cannot see it, which is exactly why loss there is often discovered late — in a changing-room mirror, a photo from behind, a barber’s pause. That same invisibility means waiting a year for the right plan costs you far less socially than waiting on a receding hairline would.
Hair Transplant on the Crown and Hairline Together
Yes, the crown and the hairline can be transplanted in the same session, and for men losing hair at both ends of the scalp it is often the most practical route. Whether it is the right route for you depends on one thing above all: whether your donor area can fund both zones properly at once.
A combined session adds the two graft requirements together. The hairline needs enough density to frame the face convincingly, and the crown, as covered above, consumes grafts faster than its size suggests. When donor supply is generous, a single procedure can treat both, with one recovery and one shedding phase to sit through. When it is tighter, spreading grafts thinly across both zones tends to leave each one looking underdone, which is the worst of both outcomes.
That is why the allocation question comes first. Most surgeons give the front priority, because it shapes your face in every mirror and photo, then assign what remains to the crown or hold it back for a later session. Some patients do better with the hairline now and the crown once that result has matured and medication has shown whether the pattern is holding.
Expect the two zones to grow on different clocks, too. The front usually looks finished while the crown is still filling in, so comparing them side by side at month six will give you a false picture of the crown. We go through graft splits, session planning and coverage targets in our guide to planning a front and crown hair transplant together.
What a Successful Crown Result Actually Looks Like — and When
Success in the crown has a specific shape and a specific schedule, and knowing both protects you from a year of unnecessary anxiety.
The shape: a successful crown reads as coverage, not carpet. Overhead light stops finding bare scalp. The whorl looks like a natural spiral rather than a flat patch. Your barber stops maneuvering around a thin spot. What it will not look like is the impenetrable density of a sixteen-year-old — no honest clinic promises that, because the donor math rarely allows it and natural crowns are not maximally dense anyway.
The schedule: the crown is famously the slowest zone on the scalp to mature. Expect shedding of the transplanted hairs between weeks 3 and 8, quiet months until around month four, visible improvement from months six to nine, and real maturation between months twelve and eighteen — often trailing the front of the scalp by a full season. This slower curve is normal crown physiology, not a warning sign, and we mapped it month by month in our crown hair transplant recovery timeline. Judge your crown at month fifteen, not month five.
How Much Does a Crown Hair Transplant Cost in Turkey?
At Hairpol, crown work is planned within our all-inclusive package for international patients, $2,500£1,900€2,250CA$3,500 with cash payment. The price is set by the technique and the package type, not per graft, and there is no graft limit or graft tier in the package.
The package includes 2-3 nights in a 4-5 star central hotel, VIP Mercedes transfers, an aftercare kit with medication, complication insurance, a guarantee certificate, a 24/7 VIP patient manager and 12 months of monthly follow-up. Payment is made in full upfront; there is no instalment or finance option. See the full breakdown on our hair transplant cost page.
How Do You Know Whether Your Crown Transplant Worked?
First, check the date. Month six tells you growth has started, month twelve is the first fair assessment, and months twelve to eighteen are where the crown does its final consolidation as hairs thicken. A large share of crowns that panic their owners at month eight are entirely normal at month fourteen, and any clinic willing to sell you a second procedure at month eight should be questioned. Judge coverage rather than counting hairs, and compare standardised photographs rather than memories; the photo routine is set out in our crown hair transplant recovery timeline.
If you are past twelve to eighteen months and the coverage is genuinely poor, the useful question is which of the two numbers failed. Poor survival across the whole field, with thin growth everywhere, points at a surgical or healing problem. Good growth in a field that is simply too small or too sparse for the area points at a planning problem — grafts spread too thin, or a crown that was always going to need more than the donor could fund in one pass. The two have different remedies. The first may justify a revision; the second usually needs a second session with a realistic graft count, or a decision to stop and manage the area medically instead through our hair treatments.
Before surgery, a few questions move the conversation from marketing language to surgical planning:
- What do you mean by success rate — graft survival, or patient satisfaction? How was it arrived at?
- What placement density are you planning at my crown, in grafts per square centimetre, and why that figure?
- Is my hair loss stable, and how did you determine that?
- What did you see when you examined my donor area under magnification?
- How many grafts can my donor area safely give, and how much of that is this session spending?
- What will my crown look like in ten years if my native hair keeps receding?
- At what point after the procedure would you be willing to say the result fell short, and what would you do then?
Vague answers to the last two are the most telling. A surgeon who has thought about your ten-year outcome will answer immediately and specifically.
Making the Decision: What to Settle Before You Book
Strip away the marketing and the fear, and the crown decision comes down to a handful of questions you can actually answer. Is your loss stable, or stabilised on medication? Does your donor area carry enough capacity for the crown and whatever the future may ask? Has a surgeon shown you healed crown results — photos at twelve months or later, under overhead light — rather than day-after implant patterns? Does the quoted graft count match the honest size of your thinning zone? And has anyone in the process told you something you did not want to hear? That last one is oddly the most reliable signal of all.
If the answers line up, a crown hair transplant is not a gamble. It is a well-understood procedure with decades of technique behind it, high graft survival, and results that genuinely hold when the planning respects the crown’s quirks.
At Hairpol in Istanbul, we treat the crown as the planning-intensive zone it is: donor mapping, whorl reconstruction, staged density where it serves the long game, and follow-up through the crown’s slow first year. If you are weighing this decision for your own crown, start with an honest assessment through our hair transplantation department — and expect straight answers, including the ones that begin with “not yet.”
Find this helpful? Add Hairpol as a preferred source on Google.
Graft Range Calculator
Answer three questions to see the typical graft range for your situation — based on our published clinical guides.
This is a preliminary estimate, not a medical assessment. The exact number can only be determined by a doctor after examining your donor area and hair characteristics.
Get a Free Consultation
Answer a few questions and the medical team will review your situation.
